




For clinicians, denture hygiene depends on more than the patient's cleaning routine. In fact, the base material and the way you build the prosthesis both affect how readily bacteria, stains, and biofilm collect on its surface.
Curious how monolithic digital dentures can support cleaner clinical outcomes? Contact the AvaDent clinical team to discuss biohygienic denture materials for your practice.
That distinction matters when you compare conventional acrylic workflows with digitally manufactured alternatives. Therefore, the link between porosity, surface integrity, and bacterial retention offers a useful starting point.
How Do Biohygienic Denture Materials Support Bacterial Resistance?
Biohygienic denture materials support bacterial resistance because they limit the surface conditions that encourage bacteria and staining. Specifically, AvaDent monolithic digital dentures use high-density PMMA in a single, dense structure. In contrast, a conventional heat-cured acrylic form stays porous. As a result, the construction can create a smoother, less retentive surface for daily care.
The clinical takeaway: a dense, low-porosity surface supports easier cleaning, but it does not replace it.
The role of a smooth, dense surface
Surface texture and material density both shape how readily deposits stay on a denture. For example, traditional denture porosity can create tiny irregularities where plaque, pigments, and debris collect. However, a monolithic process removes that porosity, so high-density PMMA offers fewer of those retention sites.
Still, this does not make a prosthesis self-cleaning. Instead, it can support better hygiene routines when you pair it with patient instruction and professional follow-up. Notably, conventional PMMA denture bases do not have built-in antimicrobial activity. In one laboratory study, for instance, an unmodified PMMA group showed zones of inhibition measuring 0 mm against the tested pathogens.
That finding reinforces an important clinical point. In short, material selection and surface design should not be described as equal to an antimicrobial treatment. You can review the full study in the published PMMA antimicrobial research.
Fewer sites for biofilm and stain buildup
A dense, monolithic surface can reduce the tiny sites available for biofilm and staining compared with porous acrylic. As a result, AvaDent positions high-density PMMA as a biohygienic material, because the design reduces bacterial and stain buildup. Even so, it does not remove bacteria or replace daily cleaning.
Clinicians can therefore frame the benefit accurately. In practice, the material may make hygiene easier to keep up. Meanwhile, the patient's cleaning technique, oral environment, denture fit, and recall schedule all remain essential.
For a deeper look at how fabrication methods affect denture material porosity, compare the surface and workflow trade-offs of printed and milled approaches. This context helps practices weigh biohygienic performance alongside fit, strength, repairability, and long-term service needs.
Monolithic vs. Laminated Acrylic: What Porosity Means for Biofilm
Porosity is a material trait with real effects on denture hygiene. For example, conventional laminated or heat-cured acrylic can hold tiny voids and surface irregularities. Consequently, these can create sites where plaque and biofilm collect. Although they do not make bacterial growth certain, they can make thorough cleaning harder over time.
Monolithic digital dentures take a different approach. Instead of layered construction, AvaDent forms the denture from high-density PMMA in a process that removes the traditional porosity of layering. As a result, a denser, less porous surface can cut the chances for bacteria and staining. However, the patient still needs hygiene instruction and professional follow-up.
Clinicians who weigh denture base material selection should therefore consider porosity alongside fit, strength, repairability, and the patient's ability to maintain the prosthesis.

A chairside comparison of the two approaches
At the chair, the practical comparison comes down to how each approach behaves over time. Accordingly, the table below sums up the key differences.
| Factor | Monolithic high-density PMMA | Laminated or traditional acrylic |
|---|---|---|
| Porosity | Monolithic manufacturing removes traditional denture porosity and supports a dense, consistent material structure. | Layered or conventionally processed acrylic may keep tiny porosity or surface irregularities, depending on fabrication and finishing. |
| Bacterial and biofilm buildup | The less porous structure can cut protected retention sites for biofilm and may help limit bacterial buildup when paired with good hygiene. | Porous areas can add retention sites, which may make biofilm removal harder for some patients. |
| Stain resistance | High-density PMMA resists bacteria and staining, which helps the prosthesis look cleaner between recalls. | Absorption and surface irregularities may add to staining, especially when cleaning is inconsistent or the finish wears down. |
| Maintenance | May support easier daily cleaning, yet still needs patient instruction, routine inspection, and proper denture-care steps. | Needs the same basic hygiene steps, plus added attention to roughness, staining, and areas where biofilm can stay. |
The clinical distinction is not that one material removes the need for hygiene. Rather, a dense, low-porosity surface can give hygiene and maintenance a better foundation. You should discuss material selection with the laboratory. In addition, you must match it to the patient's anatomy, risk factors, dexterity, and recall plan.
What Does the Evidence Say About PMMA and Bacterial Resistance?
The evidence supports a careful split between conventional PMMA and newer material strategies. First, conventional PMMA denture base lacks built-in antimicrobial activity. For example, in one laboratory study, the conventional PMMA group produced zones of inhibition (ZOI) of 0 mm against both tested pathogens. In other words, the material itself did not show measurable antimicrobial inhibition under the study conditions.
Clinicians can review the study methods and results in the published PMMA antimicrobial research.
What the evidence does and does not support
By contrast, some additive approaches show stronger laboratory performance than unmodified PMMA. For instance, PMMA infused with chlorhexidine microspheres showed the highest reported activity in the cited study. Its mean ZOI values reached 15.3 +/- 1.5 mm and 13.7 +/- 1.3 mm against the two tested pathogens.
Silver nanoparticle-infused PMMA showed moderate inhibition. Specifically, its mean ZOI values reached 10.5 +/- 1.2 mm against Streptococcus mutans and 8.8 +/- 1.0 mm against Candida albicans. These measurements point to antimicrobial activity in a laboratory assay.
However, they do not, on their own, prove long-term clinical benefit. Likewise, they do not prove safety in every patient, and they do not replace cleaning and recall steps. Other approaches remain investigational. For example, a separate study found that anatase titanium dioxide nanotubes in conventional PMMA resin showed promise against cariogenic bacteria and Candida albicans.
These findings help clinicians understand the direction of TiO2 nanotube research. Even so, you should read them as an emerging materials strategy rather than a routine clinical standard.
Where the research currently stands
To summarize the current landscape:
- Conventional PMMA: no built-in antimicrobial activity in laboratory testing, with 0 mm zones of inhibition.
- Chlorhexidine-infused PMMA: the strongest tested laboratory activity, with mean ZOI values of 15.3 +/- 1.5 mm and 13.7 +/- 1.3 mm.
- Silver nanoparticle-infused PMMA: moderate inhibition, with mean ZOI values of 10.5 +/- 1.2 mm and 8.8 +/- 1.0 mm.
- Titanium dioxide nanotubes: promising but investigational against cariogenic bacteria and Candida albicans.
Importantly, you should also separate these additive technologies from AvaDent's monolithic high-density PMMA construction. AvaDent's biohygienic rationale is structural. In other words, a dense, monolithic material removes traditional micro-porosity and reduces the sites where bacteria, biofilm, and stains can collect. It is not an antimicrobial drug-delivery system, and it should not be called infection-proof.
For clinicians who weigh advanced manufacturing technologies, the practical question is how material density, surface condition, fit, and patient hygiene work together. Together, these factors support prostheses that patients can maintain.
See how AvaDent's monolithic construction supports cleaner clinical outcomes. Browse our digital denture solutions.
In short, the literature supports continued study of chlorhexidine, silver nanoparticles, and TiO2-based changes. At the same time, it reinforces why you should separate measured antimicrobial inhibition from the broader biohygienic benefits of a precise, nonporous monolithic denture.
How Do Biohygienic Denture Materials Affect Patient Oral Hygiene Outcomes?
Material selection shapes more than denture strength and appearance. In addition, it affects how readily plaque, bacteria, and stains collect on the prosthesis. It also affects how consistently a patient can maintain the denture between visits. Generally, smoother, less porous surfaces are easier to clean, because they give deposits fewer places to collect.
Of course, that does not replace a prescribed hygiene routine. Still, it can make daily care more manageable for patients and caregivers.
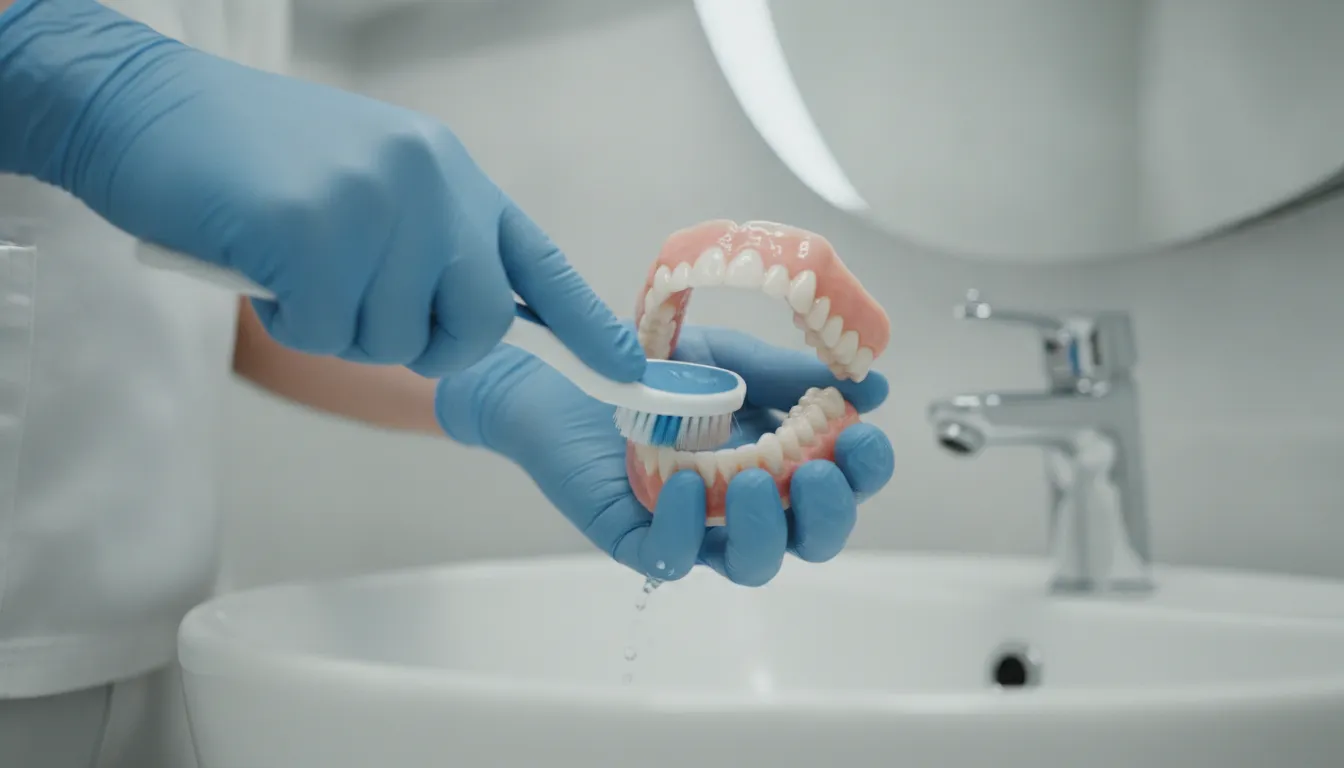
Why surface texture affects daily cleaning
Traditional acrylic processing can leave porosity inside the denture base. As a result, these tiny spaces may add retention sites for biofilm and discoloration. This is especially true when cleaning is inconsistent or the prosthesis meets staining substances.
By contrast, AvaDent's monolithic digital dentures use high-density PMMA and a process that removes traditional denture porosity. Therefore, the resulting surface can help cut bacteria and staining compared with more porous conventional materials. Moreover, it supports a predictable clinical workflow.
For clinicians, the practical outcome is not a promise of a bacteria-free prosthesis. Instead, it is a chance to pick a material that supports the hygiene instructions you already give. As a bonus, patients may find a smoother, more biohygienic surface easier to brush and rinse well.
Setting clear expectations with patients
When you set expectations, you should still assess several factors:
- The patient's dexterity and ability to follow cleaning instructions.
- Tissue health, diet, medication profile, and salivary flow.
- Denture fit and the stability of the prosthesis during function.
- The practice's recall and hygiene-reinforcement schedule.
Fit is another part of the hygiene equation. For example, a precisely fitting denture can stay more stable during function. In turn, this may help limit food trapping and reduce irritation from movement. However, it does not remove the need to check the supporting tissues, the bite, and the patient's technique.
How fit, recall, and digital records support hygiene
A better-fitting prosthesis can make routine care more practical. Even so, a structured recall process still matters. That process includes inspecting the appliance, assessing the oral tissues, and reinforcing cleaning instructions. To keep those conversations consistent, practices can use a documented denture hygiene maintenance protocol.
Digital records add a further advantage when replacement is needed. For instance, stored patient files can support quick, precise remakes. Consequently, this reduces the need to restart the design process and can limit extra chair-time. That continuity is valuable when a denture is lost, damaged, or no longer serviceable.
In combination, material density, surface traits, fit, patient education, and recall discipline create a more complete approach to oral hygiene outcomes. In the end, no single material claim can deliver that.
Why Monolithic Construction Helps Practices Deliver Cleaner Outcomes
Material performance matters clinically, because it shapes more than the finished prosthesis. In addition, it affects how efficiently a practice can deliver, maintain, and replace dentures. For example, monolithic construction uses a single, high-density PMMA structure rather than a layered approach.
Because the process removes traditional micro-porosity, it can limit the surface sites where bacteria, biofilm, and stains may collect. Still, that does not replace patient-specific hygiene instruction or recall care. Rather, it gives the clinical team a material platform that can be easier to keep clean when paired with sound maintenance steps.
The distinction is especially relevant when practices weigh monolithic digital dentures as part of a broader digital workflow.
Fewer adjustments can support a more efficient delivery appointment
A precise digital design and a consistent process aim to improve fit predictability. For example, when the prosthesis meets the planned clinical requirements, many cases need fewer adjustment cycles. Of course, the exact result still depends on the patient, records, clinical planning, and delivery technique. Even so, a predictable starting point can ease avoidable chair-time pressure.
For practices, that efficiency has operational value. As a result, clinicians can spend less time correcting preventable fit issues. Instead, they can spend more time reviewing insertion, the bite, home-care expectations, and follow-up needs. Laboratories also benefit from a repeatable process that supports clearer communication between design and delivery.
Stored digital files simplify future replacement planning
Digital records create another practical advantage. Specifically, when the patient's design files are stored, a future replacement can often start from an established digital foundation. Therefore, the workflow does not have to begin from scratch.
The replacement still needs proper clinical evaluation and updated records when indicated. However, the stored file may help the team move faster toward a precise duplicate or planned revision. In turn, this can support continuity when a denture is lost, damaged, or due for replacement.
It may also reduce unnecessary appointments. Moreover, it can help practices give a more consistent experience across the patient's treatment history. Monolithic construction is not a guarantee of a complication-free outcome. Nevertheless, its mix of high-density material, controlled fabrication, predictable fit goals, and digital file retention can help practices deliver cleaner, more manageable workflows.
Ready to evaluate biohygienic monolithic dentures for your practice? Request a clinical consultation with the AvaDent team about biohygienic denture materials.
Frequently Asked Questions
What materials are used for digital dentures?
Digital dentures can come from high-density PMMA and other CAD/CAM-compatible denture materials. In a monolithic design, for example, the denture base and teeth are milled as one prosthesis. Therefore, they are not assembled from porous, laminated layers. When you choose a material, evaluate it for fit, strength, surface traits, maintenance, and the clinical workflow it supports.
How do denture materials affect bacterial buildup?
Surface porosity and roughness can create sites where plaque and biofilm collect. By contrast, high-density monolithic PMMA reduces micro-porosity. As a result, this can help limit bacteria and staining compared with more porous acrylic. Still, this material advantage does not replace daily cleaning, professional follow-up, or proper patient hygiene instruction.
Are monolithic dentures more hygienic than traditional ones?
They can support easier hygiene, because the monolithic process removes the porosity of traditional dentures. As a result, you get a dense, integrated prosthesis with fewer areas that trap debris and biofilm. However, hygiene outcomes also depend on fit, surface finishing, patient cleaning habits, and recall care. For that reason, you should not present monolithic construction as an absolute anti-infection guarantee.
What is the best material for dental prosthetics to reduce biofilm?
There is no single best material for every case. Instead, clinicians should weigh a dense, well-finished material with low porosity alongside fit and maintenance needs. For example, research has found that conventional PMMA lacks built-in antimicrobial activity. Meanwhile, experimental changes such as chlorhexidine-infused PMMA have shown antimicrobial activity in laboratory testing. For its methods and limits, see the published study: PMMA antimicrobial research.
Contact Us About Biohygienic Monolithic Digital Dentures
When material selection, fit precision, and long-term maintenance all matter, a conversation with the AvaDent clinical team can help. In short, the team can evaluate whether biohygienic monolithic digital dentures fit your practice and patient workflow.
Contact AvaDent today to talk with the clinical team about your clinical goals and next steps.


